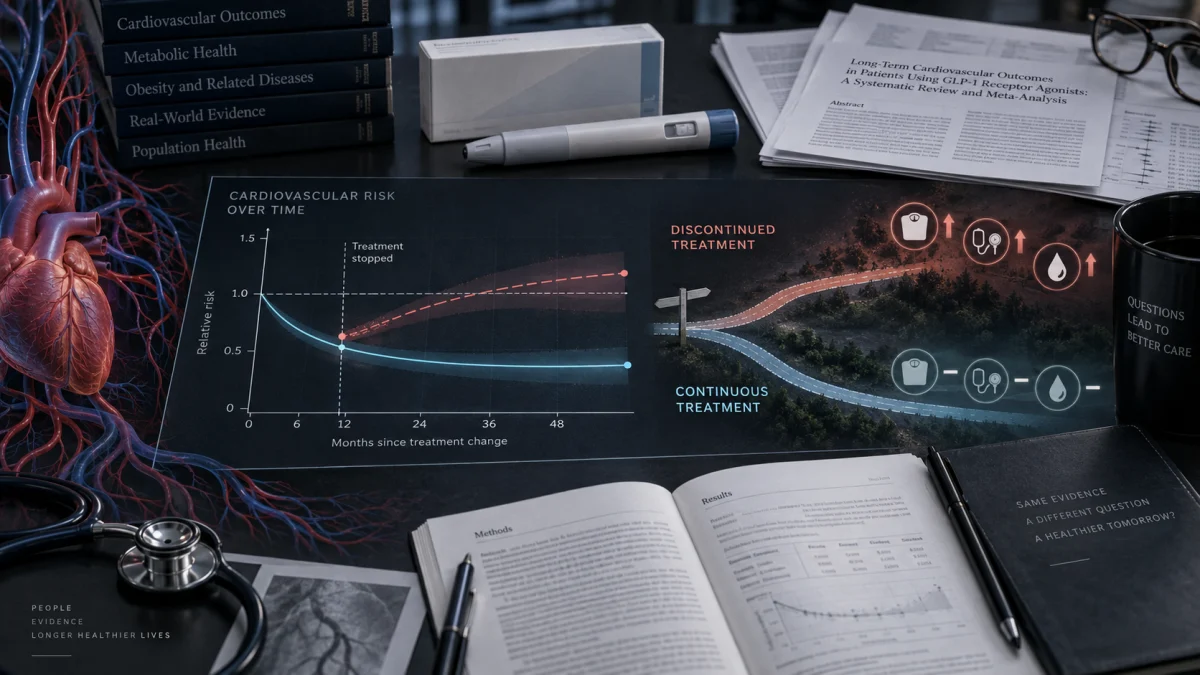
A large study did find worse cardiovascular outcomes among people who stopped GLP-1 treatment for long periods, but the viral “22% higher risk” claim needs an important qualifier: the 22% was relative to people who stayed continuously on treatment. It was not a finding that stopping Ozempic makes someone’s cardiovascular risk 22% higher than it was before they ever took the drug.
The March 2026 BMJ Medicine study followed U.S. veterans with type 2 diabetes and found that people modeled as being off GLP-1 treatment for two years had a 22% higher relative risk of a combined outcome of heart attack, stroke, or death from any cause compared with people who remained continuously on GLP-1 therapy.
That distinction matters.
The study also found that continuous treatment produced the strongest cardiovascular advantage, while progressively longer periods off treatment eroded that advantage. The results therefore support taking treatment continuity seriously. They do not, however, establish a 22% cardiovascular “withdrawal penalty” above someone’s untreated or pre-GLP-1 risk.
There are several other limitations that have largely disappeared from the headline version:
- Every person in the study had type 2 diabetes.
- The GLP-1 group averaged about 66 years old.
- Roughly 92% were men.
- The 22% outcome combined heart attack, stroke, and all-cause death. It was not a 22% increase in heart attacks alone.
- Semaglutide was common in the cohort, but tirzepatide accounted for only 0.03% of GLP-1 users, making a Zepbound-specific interpretation particularly uncertain.
- The study was a sophisticated observational target-trial emulation, not a randomized experiment assigning people to continue or stop treatment.
The strongest conclusion supported by the evidence is narrower and more useful:
Continuous GLP-1 treatment was associated with better cardiovascular outcomes, and that protection progressively weakened during prolonged interruption or discontinuation. What the study cannot determine is whether the difference represents only loss of an active treatment benefit, additional metabolic rebound after stopping, differences between people who continue and discontinue treatment, or some combination of all three.
What does the “22% higher risk” actually mean?
The number comes directly from the study.
Compared with people modeled as continuously using GLP-1 therapy for three years, those who had discontinued treatment for:
| Time off GLP-1 treatment | Relative risk vs. continuous treatment |
|---|---|
| 6 months | 4% higher |
| 1 year | 14% higher |
| 2 years | 22% higher |
The corresponding incidence risk ratio after two years of discontinuation was 1.22, with a 95% confidence interval of 1.16 to 1.27, according to the original BMJ Medicine study.
That is a meaningful association.
But relative risk always requires a reference point.
Here, the reference was continuous GLP-1 treatment, not the person’s cardiovascular risk before starting a drug such as Ozempic.
What the 22% figure does and does not mean
| Interpretation | Does the study support it? |
|---|---|
| Two years off treatment was associated with 22% greater composite risk than continuous treatment | Yes |
| Heart attacks alone increased by 22% | No |
| Stroke alone increased by 22% | No |
| Risk rose by 22 percentage points | No |
| Cardiovascular risk became 22% higher than before starting a GLP-1 | Not established |
| Continuous treatment preserved more cardiovascular benefit | Yes |
| Stopping causes a unique cardiovascular withdrawal syndrome | Not established |
This is why “stopping Ozempic raises heart-attack risk 22%” is too broad.
A more accurate description is that prolonged discontinuation was associated with progressively worse outcomes compared with remaining continuously treated.
The study’s outcome was not just heart attacks and strokes
The study’s primary outcome was a composite of:
- myocardial infarction, or heart attack;
- stroke;
- death from any cause.
The researchers refer to this combined endpoint as major adverse cardiovascular events.
That means the 22% result cannot legitimately be translated into:
“Your chance of having a heart attack increases 22%.”
The analysis did not establish a 22% increase in each component separately.
This may sound like a technical distinction, but it changes how an individual reader should interpret the headline. A composite endpoint can rise because of changes across multiple components, and the effect on any one component does not necessarily equal the effect on the composite.
The sulfonylurea comparison tells us something important about what may be happening
One of the most useful parts of the study has received far less attention than the 22% figure.
The researchers also compared different GLP-1 treatment trajectories with people taking sulfonylureas, another class of diabetes medications.
People who remained continuously on GLP-1 treatment for all three years had the strongest advantage:
- Sulfonylurea group: 20.65 composite events per 100 people
- Continuous GLP-1 treatment: 16.89 per 100
- Absolute difference: approximately 3.76 fewer events per 100 people over three years
By contrast, the study found that participants who used a GLP-1 for only six months, one year, or 18 months and then discontinued it for the remainder of the three-year period ended up with incidence risk ratios close to 1.0 compared with the sulfonylurea group, meaning the statistically detectable cardiovascular advantage largely disappeared.
Longer GLP-1 exposure preserved more of the advantage:
| GLP-1 treatment pattern | Risk vs. sulfonylurea |
|---|---|
| 2 years on, then 1 year off | IRR 0.93 |
| 2.5 years on, then 6 months off | IRR 0.85 |
| Continuous for 3 years | IRR 0.82 |
These results are reported in the original study.
This provides a much more intuitive way to understand the finding.
The results look strongly compatible with a progressive erosion of cardiovascular protection when treatment stops.
But there is a limit to that interpretation too.
Sulfonylureas are an active diabetes treatment, not a measurement of what the same patients’ risk would have been had they never received GLP-1 therapy. The study therefore cannot prove that cardiovascular risk simply “returns to baseline.”
Nor can it prove that the entire difference is merely lost benefit.
What it shows is that continuous use was associated with the best outcomes and prolonged non-use progressively reduced that advantage.
Who was actually studied?
The population matters enormously.
The study used electronic health records from the U.S. Department of Veterans Affairs and included:
| Characteristic | Study population |
|---|---|
| GLP-1 initiators | 132,551 |
| Sulfonylurea initiators | 201,136 |
| Total participants | 333,687 |
| Condition | Type 2 diabetes |
| Mean age of GLP-1 group | 65.9 years |
| Men | 91.7% |
| Mean BMI | 35.4 |
The independent editorial published alongside the study specifically cautioned that the findings still need to be substantiated in younger people, women, and people without diabetes who use these medications for obesity.
That is a major generalizability issue.
A 35-year-old woman taking Wegovy solely for obesity is not represented by this study in the same way as an older man with type 2 diabetes treated through the VA system.
That does not mean discontinuation is harmless in younger or obesity-only patients.
It means the study does not establish that their cardiovascular risk changes by the same 22%.
Was this actually an Ozempic study?
Not exactly, although semaglutide was very well represented.
The investigators studied a class of GLP-1-based drugs, rather than testing Ozempic against discontinuation in a dedicated randomized trial.
The study’s GLP-1 treatment mix was:
| Drug | Share of GLP-1 cohort |
|---|---|
| Semaglutide | 66.13% |
| Liraglutide | 18.48% |
| Dulaglutide | 13.41% |
| Exenatide | 0.98% |
| Albiglutide | 0.96% |
| Tirzepatide | 0.03% |
| Lixisenatide | 0.01% |
Those proportions are documented in the study’s published peer-review record.
Semaglutide, the active ingredient in both Ozempic and Wegovy, accounted for roughly two-thirds of GLP-1 use.
The researchers also performed a sensitivity analysis restricted to semaglutide initiators. The published study reports that its sensitivity analyses were consistent with the main findings.
That makes semaglutide much more relevant to the result than some of the broader drug names being attached to the story.
Still, molecule and indication matter.
Ozempic is approved for people with type 2 diabetes, including cardiovascular-risk reduction in adults with type 2 diabetes and established cardiovascular disease.
Wegovy also contains semaglutide but is used for obesity and overweight, and its current FDA prescribing information includes reduction of major cardiovascular events in adults who have established cardiovascular disease and overweight or obesity.
Those populations overlap with the VA cohort in some respects, but they are not interchangeable.
What about Wegovy users who do not have diabetes?
There is strong randomized evidence that semaglutide can protect the cardiovascular system in some people with obesity who do not have diabetes.
The landmark SELECT randomized trial published in the New England Journal of Medicine enrolled 17,604 adults with overweight or obesity and established cardiovascular disease but no diabetes.
A major cardiovascular event occurred in:
- 6.5% of participants receiving semaglutide;
- 8.0% receiving placebo.
The hazard ratio was 0.80, indicating a 20% relative reduction during treatment.
That trial helped establish Wegovy’s current cardiovascular indication.
But SELECT answers a different question:
Does semaglutide reduce cardiovascular events while people take it?
It does.
SELECT did not randomize successful users to stop treatment and then measure whether their cardiovascular-event rate rose by 22%.
So we have strong evidence that semaglutide can provide cardiovascular protection in a specific population without diabetes.
We do not yet have evidence showing that the VA study’s exact 22% discontinuation figure applies to every Wegovy user without diabetes.
What about Zepbound and Mounjaro?
This is where the broad headline becomes particularly shaky.
Mounjaro and Zepbound both contain tirzepatide, a dual GIP/GLP-1 receptor agonist.
But tirzepatide represented only 0.03% of the GLP-1 group in the VA discontinuation study.
The researchers explicitly told a peer reviewer that their study evaluated a class effect and did not determine whether individual GLP-1 drugs had different discontinuation effects.
So the VA study is very weak evidence for saying:
“Stopping Zepbound raises cardiovascular risk 22%.”
There is, however, important newer evidence about tirzepatide itself.
The SURPASS-CVOT randomized trial compared tirzepatide with dulaglutide among people with type 2 diabetes and established atherosclerotic cardiovascular disease.
A cardiovascular primary-endpoint event occurred in:
- 12.2% of the tirzepatide group;
- 13.1% of the dulaglutide group.
Tirzepatide met the trial’s criterion for noninferiority, although it did not demonstrate statistically significant superiority over dulaglutide.
In August 2026, the current Mounjaro prescribing information was updated to include reduction of major cardiovascular events in adults with type 2 diabetes who are at high cardiovascular risk.
The current Zepbound label, by contrast, lists long-term weight management and treatment of moderate-to-severe obstructive sleep apnea in adults with obesity. It does not currently carry the same cardiovascular indication.
The important distinction is:
Evidence that tirzepatide provides cardiovascular benefit while a patient is taking it does not establish that stopping Zepbound produces the VA study’s specific 22% increase.
That discontinuation question remains open.
Is stopping causing new harm, or are patients simply losing the drug’s protection?
The honest answer is: we do not yet know how much each mechanism contributes.
There are at least three plausible explanations.
1. The person loses an active treatment benefit
GLP-1-based therapies affect much more than appetite.
Depending on the drug and population, treatment can improve body weight, blood glucose, blood pressure and other cardiovascular risk factors, while randomized trials have demonstrated reductions in cardiovascular events in selected populations.
Stopping an effective treatment therefore removes something that was actively reducing risk.
2. Weight and cardiometabolic risk factors can rebound
This part is well established.
In the STEP 1 semaglutide withdrawal extension, adults with overweight or obesity who stopped semaglutide 2.4 mg regained roughly two-thirds of their previous weight loss within one year. Many cardiometabolic improvements also moved back toward baseline.
A much larger 2026 BMJ systematic review and meta-analysis examined 37 studies with 9,341 participants and similarly found rapid weight regain after stopping weight-management medications, along with reversal of beneficial cardiometabolic changes.
Those findings provide a plausible pathway through which cardiovascular risk could worsen over time.
3. People who stop treatment may differ from those who continue
This is the unavoidable observational-study problem.
People discontinue drugs for many reasons, including:
- side effects;
- cost or loss of insurance coverage;
- shortages;
- inadequate response;
- changes in health;
- competing illnesses;
- medication burden;
- adherence behavior.
A 2026 national survey of former GLP-1 users found cost, side effects, lack of insurance coverage and reaching a weight-loss goal among the most commonly reported reasons for stopping.
The VA investigators used extensive statistical methods to account for measurable differences between treatment groups, but they did not know why each participant stopped treatment.
That creates the possibility of residual confounding, meaning unmeasured differences could still explain part of the observed cardiovascular gap.
The study authors acknowledge this limitation, as does the accompanying independent BMJ editorial.
Is “metabolic whiplash” a proven effect?
No. It is a plausible interpretation, not a directly demonstrated mechanism.
The renewed media coverage has quoted senior study author Ziyad Al-Aly describing the consequences of stopping treatment as “metabolic whiplash” and suggesting that discontinuation may leave a “lasting scar.”
Those phrases come from the researchers’ interpretation of the findings, reproduced in the Washington University material circulated by ScienceDaily.
The underlying study did not identify an irreversible cardiovascular lesion caused by stopping GLP-1 treatment.
In fact, the researchers explicitly state that determining whether the observed association is mediated by weight regain, worsening blood sugar control, inflammation or other mechanisms requires further research.
A May 2026 review in Nature Reviews Endocrinology lays out several biologically plausible ways that GLP-1 discontinuation and repeated treatment cycling could increase cardiovascular risk. But the review also emphasizes a crucial limitation: data on hard cardiovascular outcomes after discontinuation remain sparse.
So the most defensible conclusion is:
Metabolic deterioration after stopping is well documented. A distinct cardiovascular withdrawal injury is not.
How strong is a “target-trial emulation”?
The VA study should not be dismissed as “just observational.”
A target-trial emulation is an attempt to use real-world observational data while specifying the question as if researchers were designing the randomized trial they ideally wanted to run.
The investigators defined multiple treatment strategies, accounted for changing treatment status over time, used inverse-probability weighting, adjusted for a large number of baseline and time-varying characteristics, and ran numerous sensitivity analyses.
Those additional analyses included:
- excluding early cardiovascular events;
- excluding people with previous heart attack or stroke;
- limiting enrollment to the period after semaglutide’s weight-management approval;
- restricting analysis to semaglutide initiators;
- alternative approaches to treatment adherence and statistical weighting.
The authors report that these sensitivity analyses produced results consistent with the main findings.
That increases confidence that the observed pattern is not a trivial statistical artifact.
But it still does not create randomization.
The independent BMJ editorial notes that important unmeasured differences may remain between people who continued and stopped treatment.
The fairest description is therefore:
This is strong observational evidence built specifically to approximate a causal trial, but it is not randomized proof that discontinuation itself caused every additional event.
Does stopping Ozempic or Wegovy suddenly make the risk worse?
The study cannot answer that question.
It did not compare abrupt cessation with gradual tapering.
For its treatment definitions, discontinuation meant stopping without resumption, while interruption meant being off treatment for at least 90 days and later restarting. The researchers then modeled treatment trajectories over six-month intervals.
That is very different from missing a single weekly injection.
There is also no FDA-labeled cardiovascular “withdrawal syndrome” for semaglutide.
The current Wegovy prescribing information specifically addresses missed doses. If two or more consecutive injections are missed, the label recommends restarting dose escalation at a lower dose to reduce gastrointestinal adverse reactions.
That recommendation is about safe re-escalation and tolerability. It is not a warning that two missed doses trigger an acute heart-attack rebound.
This does not prove that abruptly stopping long-term treatment has no cardiovascular consequences.
It means the new VA study did not test abrupt versus gradual withdrawal, and the 22% result should not be applied to a missed dose or short delay.
Should Ozempic or Wegovy be tapered instead of stopped abruptly?
There is currently no evidence that tapering to zero prevents the cardiovascular association found in the VA study.
In fact, researchers are now conducting a trial specifically because this question remains unresolved.
The REST randomized trial protocol is comparing two semaglutide discontinuation strategies in people with obesity:
- immediate cessation;
- reducing the semaglutide dose by 25% every four weeks until complete withdrawal.
The primary outcome is weight change, with cardiometabolic outcomes also being measured.
There are no results yet.
So claims that tapering has already been proven to protect against post-GLP-1 cardiovascular events go beyond the evidence.
What about staying on a lower dose instead of stopping completely?
This is a somewhat different question, and there is emerging randomized evidence.
The 2026 SURMOUNT-MAINTAIN trial published in The Lancet studied people with obesity who had already undergone tirzepatide treatment.
Participants were randomized to:
- remain on their maximum tolerated tirzepatide dose;
- reduce to 5 mg;
- or switch to placebo.
Both active-treatment strategies preserved substantially more of the weight-loss benefit than withdrawing treatment.
That provides evidence for lower-dose maintenance as a potentially useful strategy in some patients.
But it does not show that tapering completely off tirzepatide prevents cardiovascular events.
Those are separate questions.
If you stop and then restart, does the cardiovascular protection return?
The VA study provides an intriguing but incomplete answer.
Across the three-year models, the composite event rates were:
| Treatment pattern | Events per 100 people over 3 years |
|---|---|
| Continuous GLP-1 use | 16.89 |
| Interrupted and later restarted | 18.25 |
| Discontinued | 19.92 |
| Sulfonylurea comparator | 20.65 |
These were modeled group-level rates, not predictions for a particular patient.
The pattern suggests that people who interrupted and restarted therapy retained or recovered some cardiovascular advantage compared with those who discontinued completely, but they did not reach the result associated with uninterrupted treatment.
That does not prove that stopping causes permanent damage.
People who interrupt medication may differ in important ways from people who remain continuously treated, and the study cannot determine whether any biological change is irreversible.
A safer conclusion is:
Restarting was associated with better outcomes than remaining discontinued, but this study cannot tell us whether cardiovascular protection is completely restored or whether there is an irreversible effect of prior discontinuation.
Does this mean you have to take Ozempic, Wegovy or another GLP-1 for life?
Not as a universal rule.
There is a strong medical case for thinking of obesity treatment as long-term therapy for many patients rather than as a short course that permanently resets body weight.
The American Diabetes Association’s 2026 Standards of Care describes obesity as a chronic, relapsing disease and notes that stopping semaglutide or tirzepatide commonly leads to substantial weight recurrence and reversal of cardiometabolic improvements.
But the ADA does not say that every patient must remain on the same full dose indefinitely.
Its guidance calls for shared decision-making and discusses options including:
- continued pharmacotherapy;
- the lowest effective maintenance dose;
- intermittent treatment in appropriate circumstances;
- switching therapies;
- stopping treatment with close monitoring.
The right long-term plan depends on why the drug was prescribed, what benefits it is providing, adverse effects, cardiovascular and diabetes risk, cost, access and patient preference.
For someone using Ozempic to control type 2 diabetes or reduce cardiovascular risk, stopping has different implications from stopping a medication being used solely for weight management.
What should someone currently taking a GLP-1 take from this study?
The study provides a reason not to assume that the benefits of treatment automatically persist after the medication is stopped.
It does not provide a reason to panic over a missed injection or conclude that discontinuation automatically causes an immediate cardiovascular crisis.
The practical takeaways are:
-
The 22% figure is relative to staying continuously on treatment. It is not a 22-percentage-point increase and was not measured against each person’s pre-treatment cardiovascular risk.
-
The study’s endpoint included heart attack, stroke and all-cause death. It did not find that heart attacks alone rose 22%.
-
The strongest direct evidence applies to older veterans with type 2 diabetes. The exact magnitude has not been established in younger obesity-only users.
-
Semaglutide was heavily represented; tirzepatide barely was. Applying the exact 22% figure to Zepbound is not supported by this dataset.
-
Weight and cardiometabolic deterioration after withdrawal are real. Multiple randomized studies and systematic reviews show substantial weight regain and reversal of risk-factor improvements after treatment ends.
-
Whether tapering reduces cardiovascular risk is unknown. A randomized semaglutide tapering trial is underway precisely because that question has not been answered.
-
Medication changes are worth planning rather than improvising. People taking a GLP-1 for diabetes, cardiovascular protection or another chronic condition should discuss discontinuation and alternative treatment with the clinician managing that condition rather than relying on a viral headline.
What researchers still do not know
Despite the size of the VA study, several important questions remain open.
Researchers still need to establish:
- the cardiovascular consequences of discontinuing Wegovy specifically in people without diabetes;
- whether the magnitude is similar in women and younger adults;
- what happens after discontinuing tirzepatide in obesity-only patients;
- whether gradual tapering changes weight regain or cardiovascular risk compared with abrupt cessation;
- whether lower maintenance doses preserve cardiovascular benefit;
- how much of the apparent risk after discontinuation comes from weight regain;
- how much comes from worsening glucose, blood pressure, lipids or inflammation;
- whether GLP-1 drugs have cardiovascular effects that disappear independently of weight;
- how rapidly cardiovascular protection returns after restarting;
- whether repeated stop-start cycles carry additional risk.
Those are not minor details. They are exactly the questions someone deciding whether and how to stop treatment actually needs answered.
The bottom line
The 22% finding is real, but the most alarming interpretation of it is not.
In a large VA population with type 2 diabetes, people modeled as remaining continuously on GLP-1 treatment had the best cardiovascular outcomes. Longer periods of discontinuation were associated with progressively worse outcomes, and two years off treatment was associated with a 22% higher relative risk of the combined outcome of heart attack, stroke or all-cause death compared with continuous treatment.
The study did not show that stopping Ozempic raises a person’s heart-attack risk 22% above where it was before treatment. It did not show a 22% increase in heart attacks alone. And it did not establish the same 22% effect for ordinary weight-loss-only Wegovy users or for Zepbound, which was barely represented in the dataset.
The evidence instead points to a more measured conclusion: GLP-1 cardiovascular and metabolic benefits depend substantially on continued treatment, and at least some of those benefits fade when treatment stops. Exactly how much is lost benefit, how much is metabolic rebound, and whether some people can safely preserve the benefit through tapering or lower-dose maintenance remain important unanswered questions.
The underlying paper was published on March 18, 2026. Its renewed September media cycle does not represent a newly published study, although the questions it raises remain highly relevant.
References and Further Reading
Primary Study and Methodological Context
Xie Y, Choi T, Al-Aly Z. “Glucagon-like peptide 1 receptor agonist discontinuation and risks of major adverse cardiovascular events in adults with type 2 diabetes: target trial emulation.” BMJ Medicine, 2026
The primary VA target-trial-emulation study behind the 22% figure. Includes the treatment-duration comparisons, continuous-use results, study population and primary composite outcome.
BMJ Medicine: “Accumulation and attenuation of cardiovascular benefit with glucagon-like peptide 1 receptor agonists”
Independent editorial discussing the strengths of target-trial emulation and important limitations, including residual confounding and generalizability beyond older men with diabetes.
BMJ Medicine peer-review record for the Xie et al. study
Documents reviewer questions about causal interpretation, generalizability, individual GLP-1 drugs and the composition of the treatment cohort.
Cardiovascular Outcomes While on Treatment
Lincoff AM et al. “Semaglutide and Cardiovascular Outcomes in Obesity without Diabetes.” New England Journal of Medicine
The SELECT randomized trial showing reduced cardiovascular events with semaglutide 2.4 mg in people with overweight or obesity and established cardiovascular disease who did not have diabetes.
Nicholls SJ et al. “Cardiovascular Outcomes with Tirzepatide versus Dulaglutide in Type 2 Diabetes.” New England Journal of Medicine
SURPASS-CVOT, establishing tirzepatide’s cardiovascular noninferiority to dulaglutide in people with type 2 diabetes and established atherosclerotic cardiovascular disease.
What Happens After Treatment Stops
Wilding JPH et al. “Weight regain and cardiometabolic effects after withdrawal of semaglutide: The STEP 1 trial extension”
Semaglutide withdrawal study showing regain of roughly two-thirds of prior weight loss within one year and movement of many cardiometabolic measures back toward baseline.
West S et al. “Weight regain after cessation of medication for weight management: systematic review and meta-analysis.” BMJ, 2026
Systematic review of 37 studies and 9,341 participants examining weight regain and cardiometabolic changes after weight-management medications are stopped.
Ceriello A et al. “Causes and consequences of discontinuation of GLP1RAs or tirzepatide.” Nature Reviews Endocrinology, 2026
Detailed review of possible mechanisms linking discontinuation, metabolic deterioration and cardiovascular risk while emphasizing the limited hard-outcome evidence available after stopping treatment.
Tapering and Maintenance
“Impact of semaglutide withdrawal on cardiometabolic profile and physiology of energy balance: The REST trial study protocol.” PLOS One, 2026
Randomized trial now comparing gradual semaglutide dose reduction with immediate cessation. This is a protocol; results are not yet available.
Horn DB et al. “Tirzepatide for maintenance of bodyweight reduction in people with obesity: SURMOUNT-MAINTAIN.” The Lancet, 2026
Randomized evidence comparing continued full-dose tirzepatide, reduced-dose maintenance and withdrawal.
Current Clinical Guidance and FDA Labeling
American Diabetes Association: Standards of Care in Diabetes 2026, Obesity and Weight Management
Current guidance on obesity as a chronic disease, long-term pharmacotherapy, weight recurrence after discontinuation and individualized maintenance strategies.
DailyMed: Current FDA prescribing information for Ozempic
Current indications and dosing information for semaglutide marketed as Ozempic.
DailyMed: Current FDA prescribing information for Wegovy
Current indications, cardiovascular indication, missed-dose instructions and re-escalation guidance for Wegovy.
DailyMed: Current FDA prescribing information for Mounjaro
Current tirzepatide labeling, including the cardiovascular-risk-reduction indication added in August 2026 for adults with type 2 diabetes at high cardiovascular risk.
DailyMed: Current FDA prescribing information for Zepbound
Current Zepbound indications and missed-dose instructions. As of this article’s publication, its label does not contain Mounjaro’s cardiovascular-risk-reduction indication.
Current Media Cycle
ScienceDaily: “Stopping Ozempic may raise heart attack and stroke risk,” September 21, 2026
Documents the renewed media cycle and Washington University framing of the March 2026 study. Used here to distinguish the headline interpretation from the underlying research.
Editorial currency note: Drug labels, indications and clinical guidance can change. FDA labeling and professional guidance above were checked against versions available on September 22, 2026.